Inside The Operating Room with Heart Transplant Surgeon Dr. Brian Lima (Part 2)


 Apple Podcasts

 Spotify

 Castro

 RSS Feed

 Youtube Music
Ever wondered what it takes to pioneer a heart transplant program, or how surgeons remain both strong and loose under the crushing pressure of life-saving decisions? In Part 2 of our conversation, Dr. Lima opens up about his journey, from overcoming professional burnout to the thrill and weight of launching Long Island's first heart transplant program, against all odds. His experience offers a rare glimpse into the courage and conviction required to navigate such a high-stakes medical frontier.
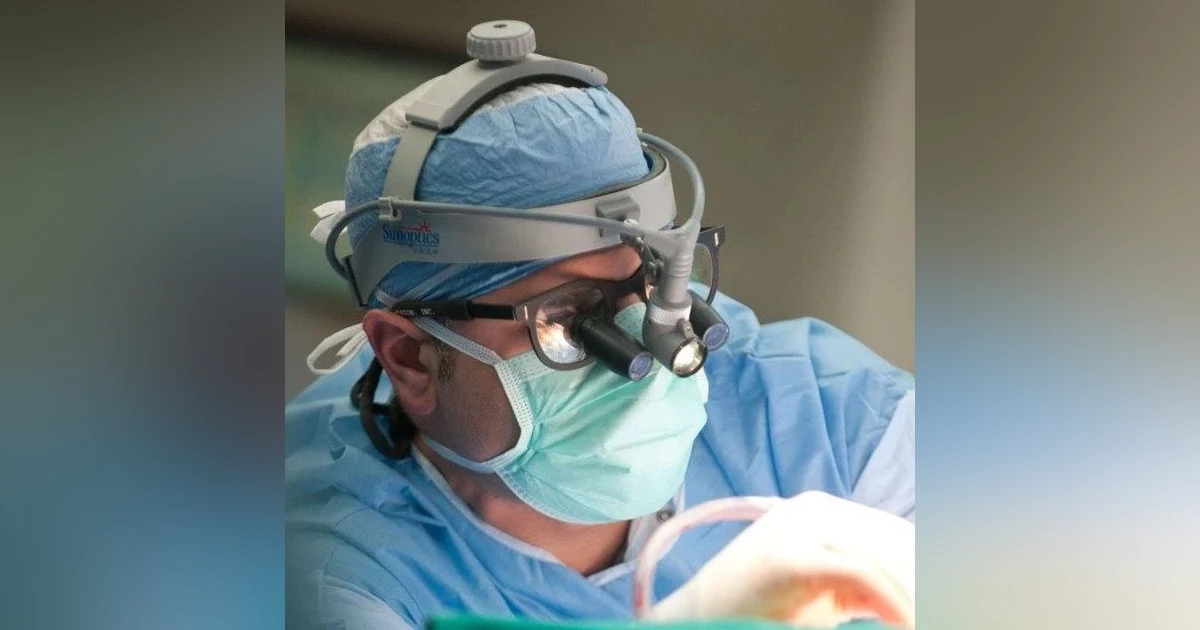
Then, Dr. Lima invites us into the operating room to reveal how transplant surgery is done. Picture a procedure as tightly coordinated as a Navy SEAL mission: it requires perfect timing, seamless team coordination, and groundbreaking techniques that offer patients a new lease on life. Here, teamwork isn't just important; it's everything.
Wrapping up, Dr. Lima shares insights that reach beyond the operating room. Whether you're in the medical field, eyeing a challenging career, or just love a good underdog story, there’s inspiration here for you. It’s about the highs, the lows, and everything in between on the path to making a real impact.
To discover more episodes or connect with us:
0:02 Hello and welcome to the Career Journey podcast no Wrong Choices, where we speak with some of the world's most interesting and accomplished people to shine a light on the many different ways we can achieve success. I'm Larry Samuels, soon to be joined by Tushar Saxena and Larry Shag. Please support our show by following no Wrong Choices on your favorite podcasting platform, connecting with us on LinkedIn, instagram, youtube, facebook X and Threads, or by visiting our website at NoWrongChoicescom. This episode is part two of our conversation with Dr Brian Lima of the Vanderbilt Medical Center. Dr Lima is a cardiac surgeon who specializes in heart transplant surgery and the author of the book Heart to Beat.
0:46 Tushar Saxena, why don't you lead us into? this one. Thank you, larry. Sam, part one was all about this notion of sacrifice, which actually is an overriding theme throughout the entire episode. But this is more about when you finally have come through that sacrifice and you've dealt with that professional burnout and now you see your career really taking off, because that's really what this is about. It's about once he kind of finds himself and centers himself. Now we'll see where the career really takes off to, because this is obviously one of the top surgeons in the country and he's found that happy balance between being a heart surgeon, which is obviously all-encompassing, and then having a life outside of that. But he is not simply Brian Lima heart transplant surgeon.
1:31 There is Brian Lima, the man behind that, and even though he always will be Brian Lima heart transplant surgeon, there has to be more to his existence than just the job. I'm so glad you just talked about that. In addition to that, we're about to get inside a surgeon's mind when he's performing an operation. I mean that is just amazing how he reveals about being in the OR and how he goes about a surgery. I mean, I just find it utterly fascinating and I think our fans are absolutely going to love it as well. Absolutely, and we learn a little bit more about the person and how he handles himself. He is definitely a comfortable, calm, cool and collected individual, and that will very much come across in this conversation.
2:18 So here is Dr Brian Lima. So now you've been nurtured, you've rested, your confidence is back and you're ready to run and fast forward 12 to 15 years. We know that you're a heart transplant surgeon, so I imagine the path forward from there was pretty exciting. So where did you go? Where did you head and how did you really dig into what you're doing now? I had always had this passion for this area of heart surgery Because I think it also translates into what I do outside of being a physician and that's kind of trying to impact public policy and kind of our system of care to improve care for these patients.
3:05 But it's such an under recognized disease and I really felt like I could make an impact in it. So I transitioned back to Baylor Dallas, which was a high volume center doing a lot of this, so I got a lot of repetition and exposure to it. But then I also was able to get back into writing about outcomes and so I created databases. I was able to write about the stuff that we were doing, which was then allowed me to be at these conferences and presenting at the podium etc. And then that actually led to being recruited by Northwell, which is kind of how we got to meet yeah where I was basically asked, hey, how would you like to start the first heart transplant program on Long Island?
3:57 And I was like, wow, wow, that's incredible, that's an incredible opportunity. And how long had you been doing transplants prior to that moment? So this was like five years into my career, five years, five years in practice. So this was a ultimate high risk, high reward venture, because the who's, who you know, murderers or whatever you want to call it in the world of medicine and in heart transplant are in Manhattan, right, and you know, you have the Mount Sinai's and the Colombias of the world all these, and they were all in opposition of Long Island getting a heart transplant program. Interesting, they actually wrote a letter of opposite, co-signed a letter of opposition to the Department of Health saying we do not believe a heart transplant program should be started on Long Island.
4:44 And so I immediately was like, okay, great, now all these heavy hitters. Wow, I feel like the Godfather music just started playing again in the background. Exactly. It sounds like a bunch of gangsters. They were all rooting for us to fail. So I was like I had to really say you know what I can do this. We're going to build a great team. It's going to be great. The whole health system was behind it. I had to write a letter of rebuttal to this letter that they wrote. They wrote I had to testify in the Department of Health and justify why we had how long was your letter? Like two words, like F and U Sounds about right. It was so crazy. But it finally came February of 2018.
5:26 We finally, the day, the night, came when we did the first one and it was magical, I mean it was incredible. It was definitely, and still is, like the proudest, you know, moment of my career because of the magnitude of that moment. You know so much had led up to it and knowing what was at stake Obviously, first and foremost, the patient, but I mean she put her trust in us too, like, I mean, that's also a big leap of faith. You know she could have just driven you know 15 miles into Manhattan and had one of these perennial kind of yeah, Babe Ruth type of thing Right.
6:06 So and it went great and it was just cameras everywhere and one of the things that came from that night was and would help kind of bring everything full circle for me when I was thinking about a book down the road or whatever, like the theme was that during that transplant again because of the magnitude of it there was video and everyone was recording and all this stuff. So things that I was doing, that I did, second nature all of a sudden became magnified and took out the old heart. You know, getting ready to sew in the new one. As I'm taking out the old heart, it's still beating in my hands. You know, wow, and it's on video because and everyone's like whoa, the heart's still beating and I'm like, and I pause for a moment and it's like, yeah, it's kind of like the heart saying wait, wait, wait.
6:56 You know, you know I can still do this. Come on, give me another shot. I was like, you know, and it's still beating a few times spontaneously and you know, typically new one sewed it in whatever. But that whole idea of, even in its last moments, the heart still trying to go and beat became kind of the foundational theme for how I tied every, all these random thoughts I had for this book and tied it all together with. You know heart to beat and all of that, so, but it was crazy, a magical, magical night and a really proud moment for me. That's so powerful. I can't wait to dig into all of the OR stuff and the surgeries.
7:37 We're going to get to that. We're going to get to that. But you know, I just I can't help but think that, because you led me right into it, the egos of doctors, right Like you're talking about these, this group from Manhattan that was against you doing this you know a doctor has to be very confident, you know, like supremely confident in what they're doing. So I don't know, do you find yourself kind of riding this wave of like Uber, confidence, superman kind of feeling and humbleness to keep you grounded and make sure that you have to get that job? I just can't imagine balancing like the power that you have when somebody's in front of you on the table. I mean that's really amazing.
8:18 But then to hear these other doctors like no, they should come here, we're better than that guy, who's that guy? You know like there's a really ego involved there. No, I mean, one of the ways I've dealt with this is that and it's because it's life sometimes has a way of reminding you just how not great you are right in this field. So every time, whenever I felt really good about myself, like oh boy, I'm, look at that, I mean, I'm on a roll, this is so good. Wham, you know, just when you think you got it all figured out, the body, you know, life, whatever will remind you you do not have everything under control and sometimes things will not go your way, even though you did everything in your mind perfect.
9:05 So I've adapted to or evolved to you don't get too high with the highs, too low with the lows. You just stay even keel. If something's going well, you're just cautiously optimistic. You're like all right, I'm not gonna good mouth it. You know, I'm just gonna, I'm just gonna ride. And we almost it's crazy in our field. You would again counterintuitive, but it's almost. We don't like it when people say, oh, he's that guy, he's doing great. I'm like whoa, easy, easy. You know, he's so far, so good, doing pretty well, you know, pleased with how things are going so far. But he's not out of the hospital yet, right. So it's superstitious maybe, but we I think it's when you get arrogant that you get dangerous.
9:49 You gotta be confident but not arrogant, and I've learned that the hard way, or whatever the hard way you wanna call it. So Are transplant surgeons. Whether are transplant surgeons, the elite of the elite of the profession, and then our heart surgeons, you know, let's say the Navy SEALs of that profession. Are you elite? Would you consider yourselves elite athletes in that sense? Well, I'm biased. He's trying to stay humble. I'm biased. We were just talking about humble too, Sean. I believe the whole thing out. I don't believe in humble. This man knows something that we we gotta get this out Well no, but actually the Navy SEAL thing. I've used this analogy because that's what drew me to it too.
10:29 You know, when you're a little med student and you're, I remember vividly, you know, on my surgery, rotations or whatever, and being with a 10th year resident or 10th year person, this person that has seen it all, done it all, you know, at midnight you're doing rounds with that person in the hospital and there's nothing that can come through the doors of that hospital that this person would not know how to handle. Right, it's just that I was like I want he's like a Navy SEAL I want to be able to feel that comfort level because I've seen it all, I've practiced, I've trained in all these different things. So, yeah, the Navy SEAL thing I think applies because outside of the brain there's really no organ in the body.
11:13 We, by the time those 10 years are up, right that we've not operated on all the blood supply to everything. And I joke also about the whole saying you know, oh, this ain't brain surgery, I think it should be, this ain't heart surgery. Heart surgery, you know the heart is a moving target. You know the brain doesn't move. You know, and at all 100 steps of a heart surgery you can kill somebody literally. I mean step one, opening the chest. If you're a little too deep, you slice the heart bleed out, you're dead. Right, I mean so all the 100-. The way you say that so nonchalantly is chillingly Wow but it's so, you know, and nothing not to take. Brain surgeons are brilliant, right, but I, in my mind, I feel, yes, that this is.
11:57 It takes a long time because there's so much at stake and it's technically so difficult and challenging. So, yeah, I think, I like to think at least that. Which leads me to the question that I've wanted to ask, which is the process. We're all curious to know. You know, how do you do not in great detail, because I imagine that would take about seven and a half hours of lecture or 10 years what's the process? I mean, how do you identify a candidate? How do you get the heart? How does the heart get from point A to point B? Like you know, I guess top-lining things to a certain degree, but what is the process?
12:39 So on the person needing it, they've obviously gone through the gamut of everything. They've exhausted all options, all conventional medications. So and the heart is the analogy I use is like you know, you could have a perfect vehicle truck, car, whatever and you could do all the right things, get the oil changes, the 40,000 mile checkup, whatever but at some point, if you drive that car long enough, it's gonna give out. And same thing applies to the heart in some respects. So the only option left is replacing the heart. So there's a system in place where, if we as a medical team feel that that person has reached that point, we list them for a heart.
13:23 And then there's a donor system, national system, and if we get a match, then we either ourselves go out and get it or sometimes there's procurement teams that go and get the heart from the donor. That's a whole other can of worms. So that's one of the questions I wanna ask, like is the heart still beating? Is it like what is the heart doing as it's traveling? So there's two kinds of donors. Historically, you know, up until three years ago, four years ago, these were brain dead donors. So, legally, you know, someone's determined to be brain dead for whatever reason car wreck, suicide, overdose, gunshot wound, et cetera they have no brain function left and a neurologist has to go and actually confirm that, yes, this person is brain dead.
14:18 In those cases it's a controlled donation, it's a scheduled thing. We're gonna tomorrow at 10 am, they're gonna go to the OR. We have five teams coming in one team from New York that's gonna take the heart, another team from Pittsburgh that's gonna take the lungs, et cetera, et cetera, and we stop the heart, take everything out and then put the heart on ice and bring it back. And when you say we, you are part of the team, that's going to get the heart. Or with the recipient, because depending on and what gets complicated is the heart really the pressure is. You really only want that process to be four hours if you can. Historically that's kinda so.
14:59 I mean you have to have the heart stopped in the donor, taken out, transported, sewn in the recipient. You want that ideally under four hours as a rough benchmark. Wow, so if it's if someone's not had heart surgery before, right, there's no scar. So I can get in and sew a heart in in an hour. On that Cause there's not. But if someone has had heart surgery before, maybe they have a heart pump, whatever it's like digging out a fossil. It's all encased in scar tissue. So it could take a good two hours, hour and a half, to get everything cleared up. I set it out so that you can take the heart out and put the new one in.
15:41 So we have to orchestrate this dance with the donor team, our team. Okay, what time? How long does it take to get from the airport to the? How long is the flight? Okay, so that means you're gonna get here. We're gonna be three hours in when you get here. Okay, that's good. That means when you get in. That means I have to have everything absolutely ready so that when you walk in the room with the new heart, boom. I could take out the old heart and sew it in. We're under the four hours Now. If it's four hours and a half or five, it's not. But I mean, these are just kind of like the rough guidelines we hold ourselves to and that's kind of what it was for ever, until 2018, when we started to look at hearts from non-brained dead people.
16:23 What does that mean? There's a large proportion of these unfortunate situations where they're not brain dead, but almost meaning for whatever reason. They still maybe have a couple of reflexes, but they're vegetables or in a vegetative state and the family is still gonna say look, we're gonna withdraw support. In that instance, you're saying is it okay if we take organs after they've died? So they pull the plug, withdraw, person dies. We then come in and take the organs. That's called donation after cardiac death.
17:03 The problem is the heart. How do you know it's okay after all of that Is you know it's the person's been dead for a few minutes. So this whole thing now of resuscitating, bringing back to life a dead heart, is what's become a big thing in our field over the last couple of years. You can either do that in the chest, where you quickly open the chest and go on the heart lung machine and see if you can get the heart back to life, or you just take the heart out and put it on an external heart and a box. Got it. That was gonna be my question. So you keep beating while traveling? And while traveling. So I did a few pioneering centers here in the United States, got going with doing that Duke and Mass General Vanderbilt, where I am now and when I came back to Texas after being in New York I did the first five or six of those in the whole state of Texas of using these donors where the person died and we bring the heart back to life.
18:09 But that's kind of the the way you can use these hearts Very, very, very big controversy right now about that in our field. It's kind of the, the hot button topic, if you will, in our field right now. So, if you're listening to this, you want this guy, you want this. This is the guy. This is the guy you want. I'm gonna steal a question that I know that my my partner here, larry Shay, was gonna ask you at some point, but it seems like the right time to ask teams and the team that you work with. You said yourself you consider yourself a Navy SEAL in some ways. Is every member of your team a member of that Navy SEAL team?
18:53 This is the ultimate team sport, I have to tell you. There's so much coordination, there's so much involved, as I mentioned just briefly. You know you have a donor team, the recipient team, and not to mention all the care leading up to that day when you know being able to take care of these people that are so sick, desperately needing a heart. They're on life support, right, they're on. So there's the team is massive. The team that decides, hey, this person is has gotten to the point where we need to do a heart transplant, doing the heart transplant itself, all of folks involved in the operating room to do that, that's it.
19:34 There's so many people. So, yeah, it's. I would. I would liken it to a Navy SEAL operation. I should say a Navy SEAL operation where you have multiple members of that team, with varying roles right, but all the roles are important. It would not be possible without all those individuals contributing. Some contribute more than others, some, you know, have more kind of oversight than others, but still, at the end of the day, it's just. It's basically a massive, you know, navy SEAL operation. So every member of that team, I'm gonna assume that you're not out there walking, walking the war. It's a warm, you're called and I don't need to joke. I don't mean it. I don't mean to be flit. You're not out there. You're not out there. You know walking the wards and doing rounds like everybody else.
20:16 So what about the other members of your team, like the nurses on your team, like they're obviously very highly specialized for transplant? I'm assuming they're not out there doing the same stuff that the average nurse is doing on the rounds? They're essentially called in. When you're called in, is that this? Is that the case? Yeah, I mean you have the operative team that are there to do the surgery. You know the anesthesiologists and you need I mean these are heart anesthesiologists, these, that these are top of the line, amazing, amazing anesthesiologists. You have the person running the heart-lung machine, because when we do these, when you do heart surgery, you have a heart-lung machine and you have a person that's sitting there at the heart-lung machine running it.
20:58 That person's amazing. Who's helping you? The scrub, the person, the nurse that's hanging near the instruments. The nurse is getting the stuff. I mean all those things. That's just the operation part. Then afterwards you go to the ICU and you have these nurses in the ICU that are highly specialized and intensive care docs that are highly specialized. That you know, because I can't be there right, you know, 12 hours after all this, this whole thing started exactly. You got a handoff. You know what they're doing. No, they're. They're keeping track minute to minute, hour to hour. Blood loss, you know, adrenaline medicines that need to be tweaked, all these different things, it's a whole. I mean it's so when you start to kind of rattle off and and consider all the people involved, it's mind-boggling but necessary For this to go.
21:48 Well, you know, obviously that's what we want. Thanks for stealing my thunder. Stealing my questions, but it's okay, it's okay, We'll roll with it. No, but he actually led me right into what I wanted to say, which is, take us more into the OR. You know, I've had a couple surgeries myself and you know I'm laying on the table and there's some Beethoven playing and they'd crack a couple jokes and then I'm out and then I don't know what happens in that room. But I'm sure you know it's not what we imagine it is. So do you like music? Do you like to be relaxing? Are you the only one speaking? Take us into the OR and really bring us through like what that moment is like. Obviously it's high pressure, but what else?
22:30 Yeah, no, I, I like music, I Depends, I'm kind of 90s time warp, I like 90s alternative or it's kind of the fault of that. You know, let's spin doctors, nirvana, whatever you know. Yeah, exactly, and Not specific to heart transplant, one of the unique, I guess pressure, you know things that drive the pressure of a heart surgery is 99 times out of 100. For the surgeries that we do, we get to stop the heart. We go on the heart lung machine, then we stop the heart for a period of time to do what we're gonna do. You could safely stop the heart and have it come back and Decent shape for a couple of hours, maybe hour and a half, two hours, but Clearly time is of the essence.
23:18 You can't be dilly-dallying, you have to be All in, but you know doing what you're doing, selling perfectly right, you know, because they can't bleed to death when you're done. So there's time pressure. So when you're on a clamp, so to speak, that means you have the heart stopped. It's like All attention, everything you know, because that that's critical, critical time. The other challenge of heart surgery as the surgeon is you have to control the whole room, all those different roles I mentioned, right at the end of the day it's. I play the position of the quarterback during those operations, so I have to know everybody's job. I have to anticipate. You know, hey, we're gonna be ready to come off to reanimate the heart in 20 minutes.
23:59 Can you get your this and this adrenaline medicine started? Hey, I'm gonna need this and this instrument. Can we get you know all? Can we make sure that the blood products are in the room to trans? So it's tense, but I've seen all flavors of how a A surgeon can conduct themselves in the operating room and the ones that I've had the most respect for and been the most kind of Influenced by are the ones that are the calmest, meaning that when things get Pretty critical they get even calmer. It's the ones that are start screaming and yelling and throwing and this and that and you, everybody gets thrown off their game. It's the ones that can take a very dire situation and and kind of relax everybody and kind of be the calm, cool and Because when you, when you get worked up, then you're not gonna be as smooth either.
24:49 So I try to abide by that kind of I Guess persona in the operating room is calm. I'm, you know, calm under pressure, not gonna flap the handle, but you have to be stern too, right? I mean, you can't be a pushover either, whose time is of the essence. You know you can't, so it's it. Navigating, that is an art, I think, of how to have the rest of your team function at their top. This, you know, I have a level of performance, but also maintain Calm and be respectful to things that used to fly. You know, a couple decades ago no longer fly, and today's I'm reamed somebody out. I got you changed world all over, for sure. Um, you talked about the Hundred steps, right?
25:31 So obviously there's a script and you want this thing to go magically by rote. You know, one Net, one thing, next thing, next thing and keep going, but things happen, things go wrong. How much of an operation is Improvisation? I know we were supposed to do this, but we have to pivot here. How much is improv? There's a thing that's evolved in what we do in all medicine, actually in surgery, called a timeout. Before you actually start the surgery, you as a surgeon say, okay, timeout, this is so-and-so, this is the plan, what we're gonna do. And I always throw in, okay, plan a is this. But if this happens and we're gonna do this, so I kind of I always go in Prepared for the worst case scenario, right so, and I have a plan so, and that comes also with time and years, so I know exactly how I'm gonna react or what the move is gonna be.
26:23 If I have run into X or Y, right, and so I prepared the team for that too, like we might have to do this in addition to what we're planning. So let's make sure we have such and such in the room in case we have to do that or this happens. There's a chance, there's. You know, I try to Statistically kind of capture what are some you know Possibilities and then be prepared for them and have the rest of the team prepared for the two, because it's unfair To just kind of keep all that to yourself too. I think you have to let the whole team in on it, like when that thing happens and you're like oh yeah, I knew this was, this is possibly I'm an NH star. Hey, I need this now, like what, what? What? You didn't prepare the team to. That falls on you. You have to kind of Quarterback and have everybody on the same page with you and be ready for those contingencies too.
27:08 As a leader, and when you describe the, the team dynamic, etc. Etc. What is the emotion and what is the the camaraderie like, like what happens after you've had a surgery. You've had a successful surgery. What is that feeling in the room with your team? you know, you know, like when the are you the types of type of guys that when you see someone celebrating the end zone after a touchdown, accessibly, you're like come on. You've been there, I haven't. You've been there before. Yes, like Barry Sanders handing the ball to the ref right class. Yeah, that's kind of what it is Meaning.
27:50 Like it's supposed to go well, right, I mean it has to go well. Like we shouldn't be surprised by this, because we plan for it, you know, same way every time is kind of one of our mantras. We have this down, you know, this is how it's supposed to go right, and High expectations. So we don't celebrate, also because that superstitious Stuff I mentioned earlier where we can't really go ahead. He did great, you know. It's like so far, so good. We still haven't left the room. Got to make sure that, you know, because Bleeding can also happen. Right, I mean, you close the chest and we have drains in place. You know that there's bleeding. That can happen later. So we want to be sure that's perfect.
28:31 So it's still a very, very Good Calm. You know, great, we'll take. We'll take the win so far, but the game is an over yet type of thing. When can you take the? win. I Think for me, if it Usually, if it goes cookie cutter by like the second day or third day got it, you will have most of the time. If something bad were to happen, you would have seen it by then. So it was first 24, 48 hours is very telling how important is the scorecard overall, meaning you know your surgery, your Surgery, for your surgery success percentage? Well, that'd be for huge, all right heart surgery is under all of heart surgery is under a microscope, but heart transplant in particular is under the biggest microscope because we are held to a standard of one year survival.
29:25 Meaning if you have a heart transplant program and and your survival after one year is not at or around 90 percent, which is kind of what's considered the national average, there's a problem. Meaning you know Medicare, medicaid, cms might come knocking on. You know what's going on like 89% means you fail no success, meaning that 90% of the people you do a transplant on are still around after you right. So I'm saying like if, but if your percentage is 89%, you know, with I mean as long as I mean, I Obviously be a little facetious, but right. I think that's the standard. But the reason why I'd say that's that's a problem or it's it's such a challenge is because you know, even if the person did great, went home, got hit by a bus six months later or something, you know, whatever it is, I mean the that's we are, and that speaks to why our selection process has to be very, very Thorough, meaning we're not only looking at Okay, is this person sick enough for a heart?
30:30 Are they gonna do well with the heart transplant? Okay, great it's also, are they gonna? Are they gonna abide by our instructions? Are they? Who's with them at home? Who's gonna help take care of them? Are they gonna? Are they reliable enough to come in for their appointments and stuff? Because we have to Make sure everything goes super, super well. It's just the high risk nature of what they have. What if the heart rejects? Two months later? We have to be doing biopsies and surveillance. So these are very. This is not a all right, got your gallbladder out. Good luck to you, you know, call it all of the years. This is a lifelong, you know, relationship that we're establishing with this, with this patient. So it is a very, very Close-knit kind of relationship that we have and For that reason, you know, we we take it extra serious, very, very serious about who we Decide is is gonna get a transplant.
31:26 I'm sitting here trying to process, like emotionally, you know what, what you must have to go through. I mean, I would imagine your Failures sit with you way more than your successes, of course. So I guess, talk to me a little bit emotionally about you know you said you took some psychology and that is part of the training. Talking to families about complications or you know this isn't gonna happen the way we thought it was. You know just that, letting them down and how you compartmentalize Emotionally when you have to have those difficult conversations, are you able to just turn around and go to dinner with your friends afterwards? I mean, it's got to be very, very challenging when things don't go right.
32:07 No, that would be amongst the most challenging of everything about this way of life. I know I went on this whole tangent earlier about, you know, my identity. Is not my job, this any other. But I Also don't look at it as a job. It is kind of a way of life and I Get very personally attached it's hard not to to each patient and it's a personal thing for me. If something doesn't go the way it's supposed to, or someone, or it doesn't go well, I'm very much up front. I Love to build good relationships with the patient, their family. I give them my cell phone, I I go right to them. I mean I don't hold anything back.
32:47 I say, hey look, this is what happened. Sorry, this happened, or whatever it is. But you're absolutely right. I mean, the failure is always. You know far fewer. But they see you hold on to those and they and they kind of Dictate how you can. You know, you'll never forget, you know that one time that this happened, I think it was because and I now, from that moment forward, I didn't do my stitch in this situation that way. I do it differently now and, right or wrong, you know, you kind of get almost Molded you evolve and you get molded by these events and you know they're learning. You learn that way, unfortunately, and so I always say, how do we get better from that?
33:31 How does that not ever happen again? Or, if the same situation presents itself, what are we gonna do differently this time around? So we do have those kinds of meetings us amongst us as a team, like, okay, you know, call it a root cause analysis or whatever kind of common quality improvement, but we are like, alright, this was something we all didn't want to happen. Why did it happen and how do we get better from it? How do we take this unfortunate tragedy and turn it, get some, extract some morsel of Positivity from it so that we can benefit someone down the road? You've. You've commented, you know, several times about not wanting things to come too close to your identity and trying to create Separation, etc. Etc.
34:12 What is the lifestyle of a heart transplant surgeon Meaning? You know, we've talked to an FBI agent before and we've asked the question. You know You're, are you, you know, always carrying a gun? Are you always engaged? And the answer is yes. Can you shut it off? Is there a space for separation, for you to walk away from the job for a little while? Like what is that dynamic? I think the answer is yes, and I think that is also played into kind of what is led to some transitions in my career. Meaning, at Northwell, right, starting the first heart transplant program for Long Island Wow, amazing.
34:53 But guess what? I was on, you know, on call for three years, yeah, literally, literally, right, I was the only person doing them right. So in our, in our program. So, yeah, I could maybe escape for a weekend to the Hamptons but be able to come to drive back if a heart transplant surfaces or something. Yeah, that is not sustainable, right. So at a place like Vanderbilt, where we do more heart transplants than anyone on the planet, we have a big team and so we can kind of Take a little time, you know, a weekend here or a week there, so we can be human, so to speak. You know you can take that time to do other, you know, and re medication like a normal, and recharge and stuff like that.
35:37 So that is important and on a day-to-day basis, when you're in the throws of kind of this, especially at a busy place like this, it's not that you can't turn it off, but you know you're not surprised if you get a call, because and that was a decision I chose to come to a place like this because I just, I don't know I wanted I've kind of almost come full circle I want to be in the throws of the Mecca of, you know, doing as much of this as possible. So if one of my colleagues is in trouble and needs help, you know, even it's not my day on call or whatever I'm gonna come in and help them or Well, you learn that from your boys, and yeah, or? whatever it is.
36:17 Hey, you know we have two transplants going at the same time. Can, are you available? Yeah, I'll come in and I'll do whatever it takes. So it's sort of it depends on the day I go. I try to, I'm trying to be more on living in the present. I think that that was also a big departure. I was always wired future, future, future. I got to do this, to get to this, so that I can achieve this and get them. Now I think it's more about being living in the present, enjoying the current moment. I'm getting to talk to you guys and having a good time, and this is pretty neat, right? Not constantly thinking about Okay, yeah, so I got to do this so that then I can Ride the ladder and ascend to this other thing.
37:02 It's no, you know, tomorrow is not promised. You got to make the most of today, and that's something that is New for me. I would say in the last few years that I've evolved to that I was more of a maturity thing and not constantly being overcome with how do I continue down this rabbit hole or on this hamster wheel. Was that some of the impetus behind writing your book? Heart to beat it was. It was such a cathartic thing to do it and I, I had all these. I had no reason. I I still do not understand why I accumulated all these random thoughts or Observations and it finally came to a point where you've been doing this stuff alone. Yeah, I got to get this out on.
37:43 I think it can help people. I don't know, I read David Goggins book can't hurt me and that was really impactful For me and I felt like I could tell a somewhat similar, analogous story. But from my perspective and through what I went through, and I don't know, I felt like maybe Some learning lessons that I experienced along the way could help other people. Because it's I don't have it figured out, I haven't yet figured out, and I thought, you know, and I think most of us do, when we're young, like all right, once I get to this, I'm gonna achieve, I'm gonna get my MBA or I'm, and then then it's I'm set, you're never, never set.
38:24 It's like that's the, that's the biggest fallacy, I think, of being young and thinking I achieved this goal and I'm done, it's you're never done. Right, we're always learning, we're always improving continuously. So that's kind of how things have gotten there. Are you? Do you still? I mean, I think you like the job that you do, but let's say the industry is a whole medicine as a whole. Are you still happy with with medicine overall, the way, the way things are? no Meaning. That's kind of also why, on the side here, I've about to get my MBA. I'm like one class away and Partly was because when you're in the midst of training to do whatever your craft is going to be, you have no idea about this other whole world that exists Outside of what you're doing in the operating room.
39:19 It's the business of medicine, right, how do hospitals run? How are things paid for? Who pays for it? All access to care, all these different things. And that really hit home when I Finally got out into the real you know market and and was just kind of you that has another commodity and All that stuff. And I was like I don't know any of this stuff, I don't. And so that's what drove me to say you know I, if I'm gonna make a difference in health care in general or whatever segment of health care that I'm really interested in, I need to bone up, I need to understand these things, I need to right. So that's what led me to Pursue this MBA, just because I want to be able to talk At the same level with the, the C-suite people, and understand what they're talking about and know kind of what drives them right.
40:10 It's not as simple, unfortunately, from my perspective, as taking good care of patients right, it's right, much, much, much more than that. It's not so simple, so I want to understand it to be able to help improve it. Are you the world's best player at operation? I haven't tried it. It'd be interesting to see how I would. I haven't tried it. Oh, get out of here. You haven't tried it. Come on it's been some time, but I've you, I've been told the game to try that is very funny. you know, my son just got the game operation as a gift. He he's five and it just so happens my wife is a surgeon, so we have a ringer in the house. It's very funny. It will not play with her.
40:50 What is your favorite medical show? Do you have one? Oh, medical show Mmm. I actually hate all the medical shows for the most part, oh I like. Why does everyone hate you? Why do you guys all hate I like, I like because it's fake. You're talking now. You're talking you know no, the movie malice With Alec. Baldwin, that's very funny. You want to know something here funny Talking about it before we started this interview. This is exactly what I was talking about with these guys. I'm like you know what? I want to ask what this movie malice and does he think of himself as Alec Baldwin? He says you know they're praying to. When they're praying to God, they're praying to me.
41:32 Very impactful. Actually. I kind of already made up my mind, but I was like, wow, that he's obviously taking in a little too far. But I was like, wow, he is. He's pretty cool, it's pretty intense though. I love that movie. I think it's really. I'm glad you said that. We knew the title. We'd never seen the movie. Oh, watch this movie. Watch this movie okay. so have you ever been, let's say, at a restaurant or on a plane? And you've heard the words is there a doctor in the house? Hmm, what do you do in that instance? You have to respond, do you know?
42:13 Yeah, I believe you do, but Never, never on a plane. I think I was in a restaurant in Manhasset one time when someone was choking on Food or something or you know having a seizure. I can't remember, but it just so happened. It was like a convention of E&T docs, you know and and they were at that, I think, like the next table over, and it was like a. There wasn't even like a me cuz like 17 doctors descended on. That's great. Lucky person At this point in the conversation.
42:56 We always ask our guests to. You know, impart some wisdom and some advice to people who Might want to fall. You know, follow in your footsteps. I imagine if we get a million listeners to this podcast, one of them will want to follow in your footsteps. So you know somebody who wants to get into your profession, somebody who wants to get into to Medicine today. You know, what type of advice do you have for them? I would say I love what I do and I would recommend it a million times over. You just have to want it for the right reasons and If you want to do it, you can do it. You'll have to work hard and never settle for, you know, for complacency.
43:37 You, there's always room for improvement. You just have to. You know you can get there. If other people could do it, you could do it too. You have to believe in yourself, but it takes time and practice and and and humility to do it, but you could do it incredible advice. Well, brian, you know. Thank you so much for the time today. Everybody out there the book heart to beat. You're gonna want to look for that, brian. I imagine it's. It's available everywhere books are found. Yes. Amazon in particular. Yeah, Is it on audiobook? No, not, didn't have the time to do it, so not everyone. Yeah, you should narrate it Come on. You had to blow it up to show, Maybe. Maybe you need to hire a VO guy to just agree to it Only 24.
44:22 Maybe, maybe that's next Next project, yeah. So, brian, thank you. This has been a remarkable conversation, so interesting. You've opened your eyes to so many different things that we've really never thought about before. So, brian, thank you so much for joining us today. It's been a pleasure. Guys, thank you, I've had a blast. So that marks the conclusion of our conversation with Dr Brian Lima, and my expectations were incredibly high going into that, and I can honestly say that they were met. Larry Shea, what are some of your thoughts? That if I have to be on a slab and have somebody open me up, I would like it to be this guy Pretty much. I mean how powerful was the moment when he talked about opening up the chest and like taking the heart out and it was still beating.
45:08 I mean amazing. I mean what a phenomenal interview. But I mean my biggest takeaways. I mean let's think about it in terms of our professional lives and our career paths. He talked about love. What you do, you know you have to want it for the right reasons. I think those are such valuable lessons that we sometimes lose sight of. And he also talked about never settling and believing in yourself. You know this is a very big challenge to do this kind of work and you know I consider myself very accomplished professionally. But the amount of information that he had to to get under his belt and to know like the back of his hand and just like I don't know, I couldn't imagine an endeavor such as this and accomplishing it.
45:54 And he's an amazing guy and just really impressive to hear him talk about all of this, because I don't think I don't think it's something that anybody could just do. I think you got to kind of be built for this. I think you're probably right about that. I will say this knowing that every time he learns one new thing, something else leaves him. That was great. I was right. I do wonder what it is to forget how to make a sandwich like a, like walking in the kitchen one day Well, what is this bread I'm using now? That's that's one thing. But you know you weren't just saying, you're saying the correct thing there, Lara, and that you know the the sad almost said again the sacrifice that it takes to reach the heights of this profession. They are extreme.
46:35 But the one other, though, the other piece of advice that he had which I thought was so telling was you know, it's OK to take an unconventional approach to your career, right, If you? If you feel that being in public practice is burning you out, well then maybe it's OK to go into private practice and have actual real hours that you deal with and have actual real and try to have an actual real life. This is not a bad thing and you know, obviously this is not. This is not 20, 30 years ago, where it was more of a, was more like being in the Marines, where now you actually, you know you can have something more of a life. But he has found that proper balance to it and I will say this you know, he, he, I always thought of doctors at that level, as a doctor, as elite athletes.
47:22 He's correct, they're more like, they're more like Navy SEALs because of that kind of precision, that kind of planning that goes where they literally are trying to storm beaches. Every time they have an operation like this. They are literally doing a real kind of military, pseudo military operation. When they're heading into the or. Everything has to be planned up precisely. Everyone has to know their job and everyone has to know everyone else's job as well. It's amazing. Absolutely. And as I look back on the conversation and you guys have have wrapped things up extremely well I'm just going to sort of grab it a few strings or straws here. You know, one of the things that I found so compelling was when he came to New York and when he came to Northwell and Long Island and some of the challenges that he had to deal with setting up a practice in this area where all in New York, I should say that, for heart transplants, like you know, he was the guy.
48:14 He was the first one out there. I mean, he was a pioneer for this region, which has to be thrilling, it has to be scary and a whole bunch of other things, and then add on top of that the dynamics and the politics of New York City. You know it. Just, it really showed me a lot about him in terms of his metal. You know, it's not just the fear and the challenge of taking on this, this massive endeavor. You have to have the politician in you to to work your way through all of this other stuff, and that takes a very special kind of person. So, dr Brian Lima, thank you so much for joining this episode of no Wrong Choices and, I should point out, for anybody who wants to get his book Heart to Beat, it is available everywhere.
49:01 We also thank you for joining us. If this episode made you think of an inspiring person in your life who could be a great guest, please send us a note via the contact page of our website at knowwrongchoicescom. We also encourage you to connect with us on LinkedIn, instagram, youtube, facebook X and Threats. On behalf of Tushar Saxena, larry Shea and me, larry Samuels, thank you again and always remember there are no wrong choices on the road to success, only opportunities, because we learn from every experience.